

Posterior Tibialis Tendon Dysfunction | Diagnosis & Treatment for Physiotherapists
Posterior Tibialis Tendon Dysfunction | Diagnosis & Treatment for Physios
Posterior tibialis tendon dysfunction, abbreviated as PTTD, is the major cause of an adult acquired flatfoot deformity and medial ankle pain. It is caused by chronic overuse and subsequent tendon inflammation which may impede tendon degeneration in later stages. The prevalence of stage I and II posterior tibialis tendon dysfunction were reported to be 3.3%-10% in women over 40. This prevalence increases with age.
An inflammatory process in or around the posterior tibialis tendon (tendinitis or tenosynovitis) usually lies at the base of symptoms. Repetitive microtrauma due to for example overpronation of the foot has been described to lie at the base of the condition.
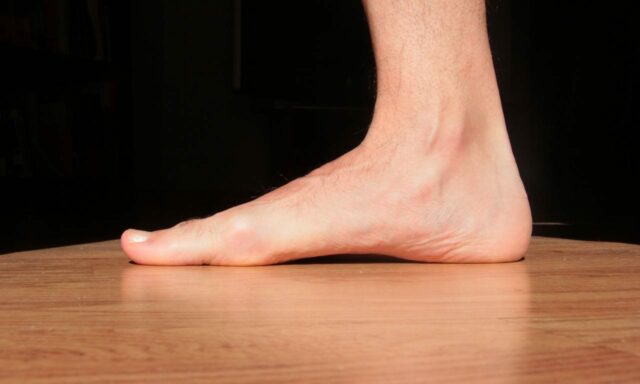
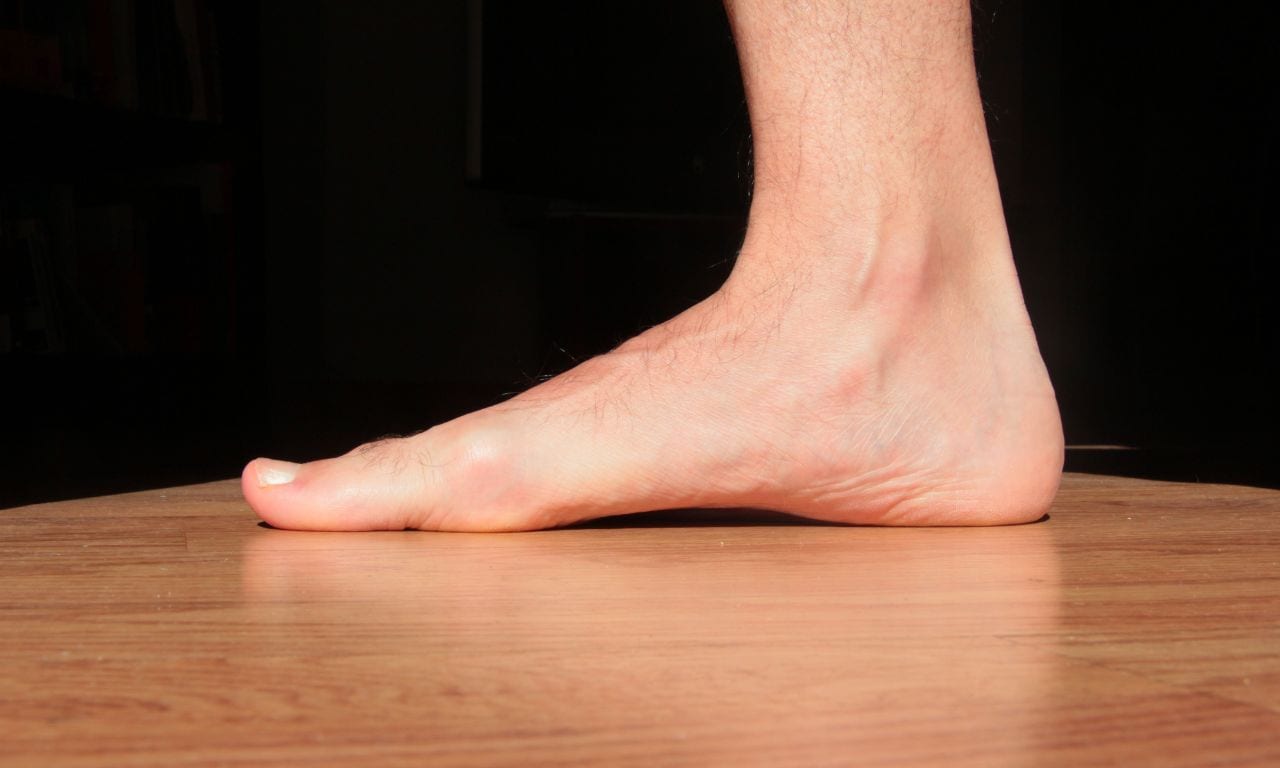
This leads to loss of function of the posterior tibialis tendon and collapse of the medial longitudinal arch. This increases strain on the medial foot and ankle ligaments. Gradually, the medial ligaments (deltoid ligament and calcaneonavicular ligament) become elongated and flatfoot deformity is acquired. It may gradually become chronic and can be accompanied by degenerative changes in the tendon. Acute trauma is rarely the cause of PTTD.
4 stages have been defined:
- Stage 1 presents with swelling and tenderness behind the medial malleolus along the course of the posterior tibialis tendon. The foot is flexible and the medial longitudinal arch is maintained. In this stage, a slight weakness and pain with inversion of the foot may be present.
- Stage 2 presents with less swelling, but a collapse of the medial longitudinal foot arch becomes evident. In this stage, the foot is flexible and the flatfoot may be corrected. It becomes gradually difficult or almost impossible to invert and plantarflex the foot and single-leg heel raise may be affected.
- In stage 3, fatigue, aching in the leg together with a reduced walking capacity becomes evident. The flatfoot deformity becomes rigid and cannot be corrected. Loss of ability to invert and plantarflex the foot is the hallmark sign.
- With stage 4, alongside the fixed flatfoot deformity, lateral ankle pain may develop due to fibular impingement against the sinus tarsi. Instability and limping may be present.
Get the 21 most useful orthopedic tests
Download our free e-book with the 21 most useful orthopedic tests per body region, to help you reach the right diagnosis.


